







No products in the cart.

Retatrutide vs. Tirzepatide: The Ultimate Weight Loss Comparison

Table of Contents
Retatrutide vs. Tirzepatide: Which Is More Promising for Weight Loss?
The rapid development of incretin-based therapies has transformed metabolic research, but few comparisons have generated as much interest as Retatrutide vs Tirzepatide.
Both compounds are being investigated for their ability to influence metabolic pathways associated with body weight, glucose regulation and energy balance. However, they approach these biological targets differently.
Tirzepatide is a dual GIP/GLP-1 receptor agonist and an established pharmaceutical therapy in several markets. Retatrutide is an investigational triple agonist designed to activate GIP, GLP-1 and glucagon receptors.
That distinction is critical.
Retatrutide has produced particularly impressive weight-loss results in clinical research, making it one of the most closely watched investigational metabolic compounds. Tirzepatide, meanwhile, has accumulated a much larger body of clinical and real-world experience and has regulatory approvals for specific indications.
So, which is better?
The answer depends on what “better” means.
If the question is maximum weight-loss potential demonstrated in clinical research, retatrutide is extremely promising.
If the question is established clinical use, regulatory status, available safety data and practical experience, tirzepatide currently has a major advantage.
This guide examines Retatrutide vs Tirzepatide from the perspectives of mechanism, clinical evidence, weight loss, side effects, dosing research, fat and lean-mass changes, storage, quality control and regulatory status.
«Research-use disclaimer: Retatrutide is an investigational compound and is not approved as a general weight-loss treatment. Research peptides discussed by NovaSyn Labs are intended for legitimate laboratory and scientific research and are not intended for human consumption or self-administration.»
Retatrutide vs Tirzepatide at a Glance

| Feature | Retatrutide | Tirzepatide |
| Primary classification | Triple receptor agonist | Dual receptor agonist |
| Main targets | GLP-1, GIP and glucagon receptors | GLP-1 and GIP receptors |
| Weight-loss research | Highly promising | Strong clinical evidence |
| Clinical development | Investigational | Established pharmaceutical therapy |
| Regulatory status | Investigational | Approved for specific indications in multiple markets |
| Mechanistic approach | Triple agonism | Dual agonism |
| Human clinical evidence | Growing | Extensive |
| Research interest | Very high | Very high |
| Common GI effects | Reported in clinical studies | Commonly reported |
| Long-term evidence | Still developing | More mature |
| Practical advantage | Potentially greater metabolic effect | Greater clinical experience and availability |
| Research handling | Requires controlled storage and verified identity | Requires controlled storage and verified identity |
Bottom line: Retatrutide may offer greater weight-loss potential based on emerging clinical data, while tirzepatide currently has the advantage in regulatory approval, accumulated evidence and clinical experience.
What Is Retatrutide?
Retatrutide is an investigational synthetic peptide designed to activate three metabolic hormone receptors:
- GLP-1
- GIP
- Glucagon
This is why retatrutide is often described as a triple agonist.
The compound has attracted enormous research interest because it combines pathways that may influence appetite, glucose metabolism and energy expenditure.
GLP-1 receptor activation is associated with appetite regulation and glucose-dependent insulin secretion. GIP signaling also plays an important role in metabolic regulation, while glucagon receptor activation has been investigated for its potential effects on energy expenditure and lipid metabolism.
The theoretical appeal is therefore straightforward:
One compound → three receptor pathways → potentially broader metabolic effects.
However, a promising mechanism does not automatically mean that an investigational compound is safer or more effective than an approved therapy.
That is why the Retatrutide vs Tirzepatide comparison needs to look beyond receptor count.
What Is Tirzepatide?
Tirzepatide is a synthetic peptide-based medicine that activates both:
- GIP receptors
- GLP-1 receptors
It is therefore classified as a dual GIP/GLP-1 receptor agonist.
Tirzepatide has been extensively studied in clinical trials involving type 2 diabetes and obesity/overweight populations.
Its development has made it one of the most important examples of how combining incretin pathways can produce substantial metabolic effects.
Unlike retatrutide, tirzepatide has moved beyond the investigational stage and is commercially available as an approved medicine for specific indications in markets including the United States, European Union and United Kingdom, subject to local labeling and regulatory requirements.
That gives tirzepatide an important advantage when comparing the two compounds.
Retatrutide vs Tirzepatide: How Do Their Mechanisms Differ?
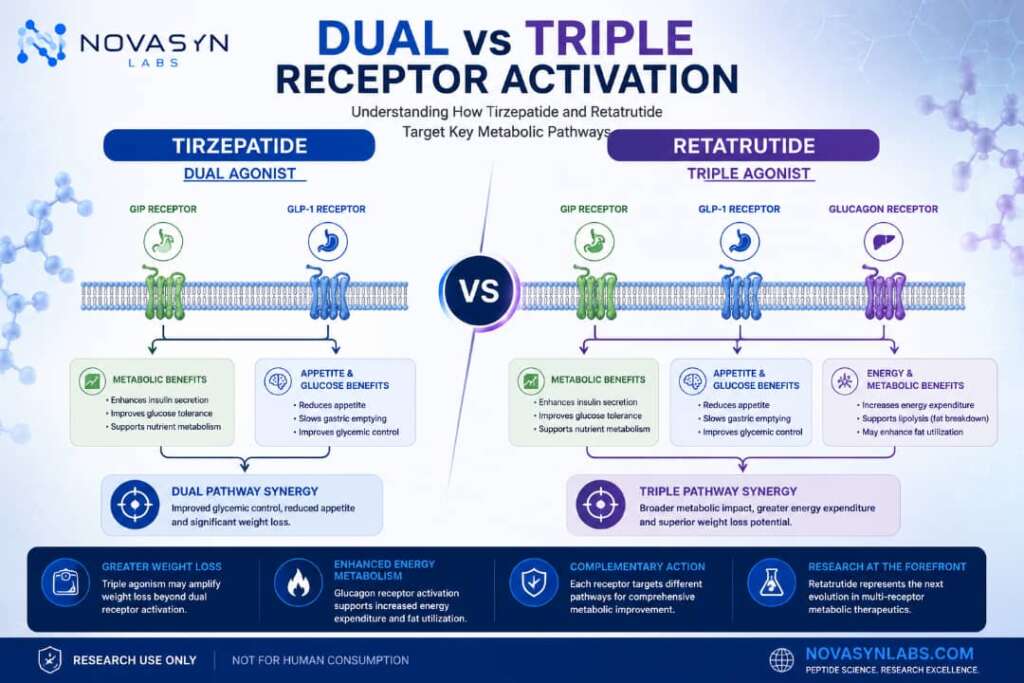
The most fundamental difference is the number and type of receptors targeted.
Tirzepatide: Two pathways
Tirzepatide activates:
GIP + GLP-1
Retatrutide: Three pathways
Retatrutide activates:
GIP + GLP-1 + Glucagon
This additional glucagon receptor activity is one of the most important areas of interest in retatrutide research.
Why does glucagon matter?
Glucagon has traditionally been associated with increasing hepatic glucose output. However, glucagon signaling also participates in broader energy metabolism.
Researchers are investigating whether carefully balanced glucagon receptor activation can contribute to increased energy expenditure and changes in lipid metabolism when combined with incretin signaling.
This creates an interesting research question:
«Can adding glucagon receptor activity to GIP and GLP-1 agonism produce greater weight-loss effects than dual GIP/GLP-1 agonism alone?»
The clinical development of retatrutide is, in part, an attempt to answer that question.
Retatrutide vs Tirzepatide for Weight Loss
This is where the comparison becomes particularly interesting.
Clinical research has demonstrated substantial weight reduction with tirzepatide. In major SURMOUNT studies, higher doses of tirzepatide produced average body-weight reductions reaching roughly the high-teens percentage range over longer treatment periods in adults with obesity or overweight, depending on the study population and treatment duration.
Retatrutide has produced even more striking results in its clinical development program.
In a phase 2 obesity study, higher-dose retatrutide produced average weight reductions approaching 24% at 48 weeks in the reported study population.
These results generated considerable interest because they suggested that triple receptor agonism could potentially produce weight-loss levels beyond those observed with many existing pharmacological approaches.
However, direct comparisons require caution.
Retatrutide and tirzepatide have not simply been placed head-to-head under identical conditions in the same large-scale randomized trial.
Therefore:
You should not interpret results from separate trials as proof that one compound will produce exactly a certain percentage more weight loss than the other in an individual person.
Trial populations, treatment duration, dosing schedules, baseline characteristics and study designs can all influence outcomes.
Weight-Loss Evidence: Retatrutide vs Tirzepatide
| Factor | Retatrutide | Tirzepatide |
| Clinical weight-loss signal | Very strong | Very strong |
| Maximum reported results | Approximately mid-20% range in phase 2 high-dose data | High-teens to low-20% range depending on study/duration |
| Evidence maturity | Earlier | More extensive |
| Large phase 3 evidence | Developing | Extensive |
| Direct head-to-head comparison | Not established as of the current evidence base | Not established against retatrutide |
| Long-term data | Limited compared with tirzepatide | More developed |
| Regulatory approval for obesity | Investigational | Approved in relevant markets/indications |
The important takeaway
Retatrutide currently looks more promising in terms of maximum weight-loss potential, but tirzepatide has substantially more established clinical evidence.
That distinction should remain at the center of any responsible Retatrutide vs Tirzepatide comparison.
Retatrutide vs Tirzepatide: Clinical Trial Evidence
Tirzepatide Clinical Evidence
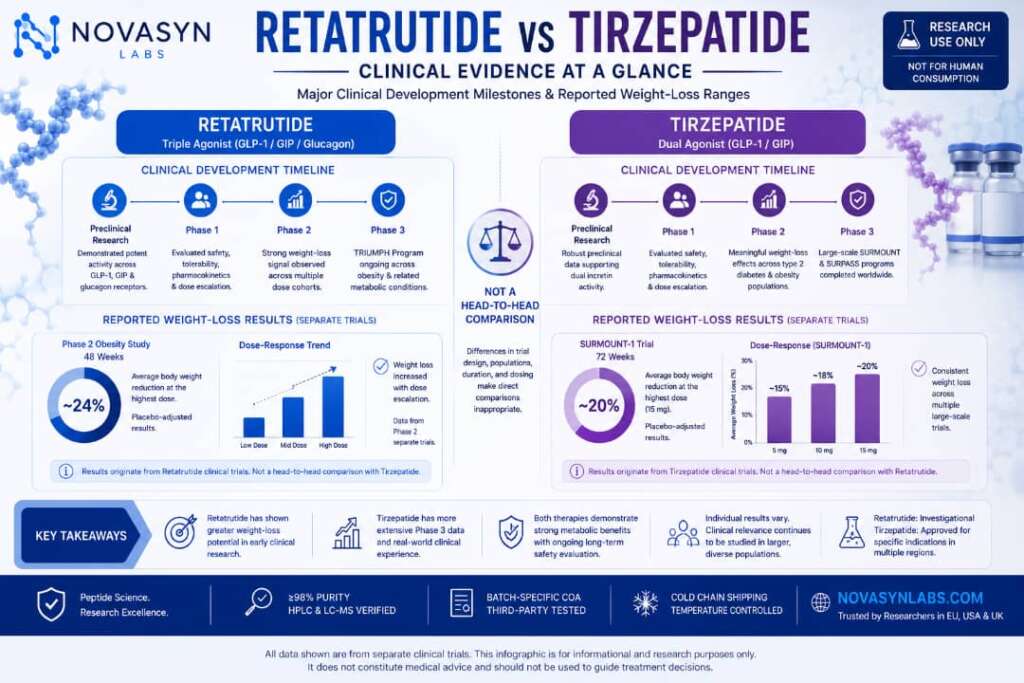
Tirzepatide has been evaluated through a large clinical development program.
The SURMOUNT program investigated tirzepatide in people with overweight or obesity, while SURPASS studies focused heavily on type 2 diabetes.
Across these studies, tirzepatide demonstrated substantial effects on body weight and glycemic measures.
The evidence base is therefore relatively mature.
Researchers and clinicians can examine:
- Different dose levels
- Long-duration treatment
- Body-weight changes
- Waist circumference
- Glycemic measures
- Adverse events
- Treatment discontinuation
- Cardiometabolic outcomes
- Weight maintenance and regain
That breadth is one of tirzepatide’s greatest advantages.
Retatrutide Clinical Evidence
Retatrutide is earlier in its development.
The phase 2 obesity trial produced particularly notable weight-loss results and helped establish retatrutide as one of the most promising next-generation metabolic compounds.
Its phase 3 TRIUMPH development program is designed to provide additional evidence across obesity and related metabolic conditions.
The most important question now is whether the impressive weight-loss signal observed during earlier research translates into:
- Consistent results across larger populations
- Acceptable tolerability
- Durable weight reduction
- Favorable cardiometabolic outcomes
- A clinically useful benefit-risk profile
Until those questions are fully answered, retatrutide should remain classified as investigational.
Dosing: Retatrutide vs Tirzepatide
Dosing is another area where readers must distinguish between clinical trial protocols and treatment recommendations.
Tirzepatide has established dosing schedules under approved prescribing information. In obesity treatment, treatment is generally initiated at a lower dose and gradually increased according to the approved product labeling and clinical guidance.
Retatrutide has been studied using different dose levels and escalation approaches in clinical trials.
These research protocols should not be interpreted as instructions for self-administration.
For research purposes, the important point is that dose-response relationships are being actively investigated.
Why gradual escalation matters in clinical research
Both compounds can produce gastrointestinal adverse effects, particularly as exposure increases.
Researchers therefore pay close attention to:
- Dose escalation
- Treatment duration
- Tolerability
- Gastrointestinal symptoms
- Treatment discontinuation
- Body-weight response
A higher dose is not automatically a better dose.
Retatrutide vs Tirzepatide: Side Effects
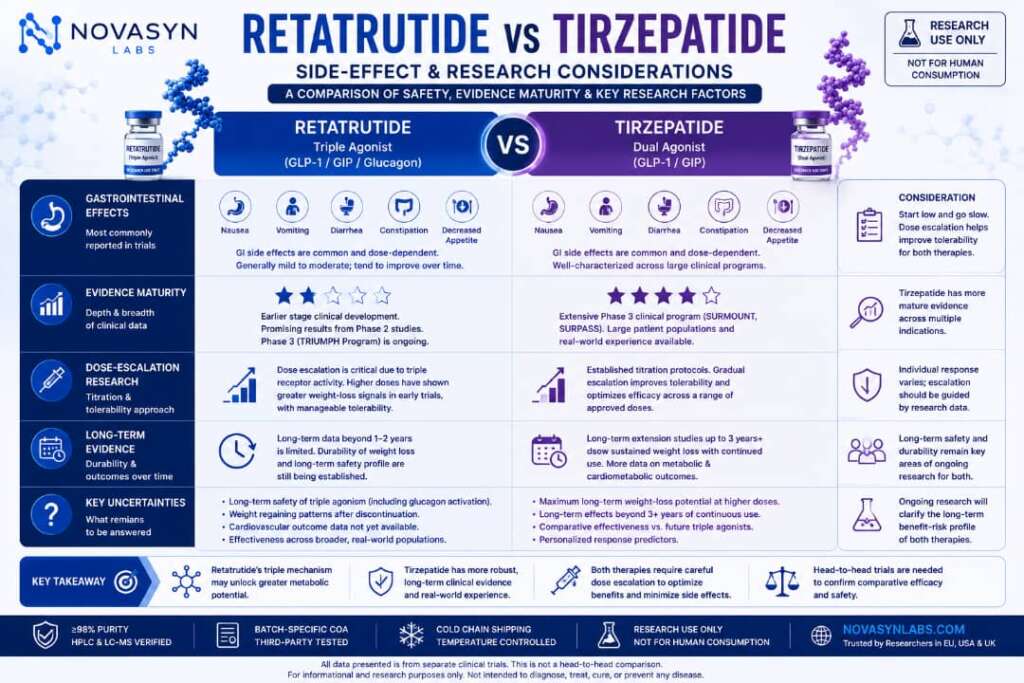
The two compounds have overlapping adverse-effect profiles because both involve GLP-1 receptor activity.
Reported gastrointestinal effects include:
- Nausea
- Vomiting
- Diarrhea
- Constipation
- Abdominal discomfort
- Reduced appetite
The frequency and severity can vary depending on dose, treatment duration and individual characteristics.
Retatrutide’s additional glucagon activity creates another important research consideration because researchers need to establish whether triple agonism produces a different overall tolerability profile.
Tirzepatide’s advantage
Tirzepatide has considerably more accumulated safety data.
Retatrutide’s limitation
Retatrutide’s safety profile is still being established through ongoing clinical development.
Therefore, it would be premature to claim that retatrutide is definitively safer—or less safe—than tirzepatide.
Fat Mass vs Lean Mass: An Important Difference
Weight loss should not be evaluated solely by the number on a scale.
Researchers increasingly examine body composition, including:
- Fat mass
- Lean mass
- Visceral adipose tissue
- Waist circumference
- Total body weight
Both tirzepatide and retatrutide studies have investigated changes beyond simple body-weight measurements.
A major research question is whether a large percentage reduction in body weight is accompanied by a favorable reduction in fat mass while preserving as much lean mass as possible.
This is particularly important because substantial weight reduction can involve some loss of lean tissue.
Therefore, when comparing Retatrutide vs Tirzepatide, a more sophisticated question is:
«Which compound produces the most favorable change in body composition rather than simply the largest change in total body weight?»
Future long-term studies will be particularly important in answering that question.
What About Weight Regain?
Another issue frequently overlooked in weight-loss discussions is what happens after treatment stops.
Obesity is a chronic metabolic condition, and discontinuing effective pharmacological therapy can lead to weight regain.
Research involving incretin-based therapies has demonstrated that maintaining weight loss can require continued treatment and long-term management.
For retatrutide, the long-term evidence base is still developing.
This means there is currently much more uncertainty surrounding long-term weight maintenance after retatrutide discontinuation than there is for an established medicine such as tirzepatide.
The bigger research question
The ultimate measure of success may not be:
“How much weight can the compound help reduce?”
It may instead be:
“How effectively can clinically meaningful weight reduction be maintained over many years while preserving health and lean tissue?”
That is an area where future data will be extremely important.
Retatrutide vs Tirzepatide: Storage and Handling
For laboratories working with research peptides, quality doesn’t stop at synthesis.
Storage and handling can directly influence the integrity of a peptide sample.
Both compounds require controlled handling according to the manufacturer’s validated specifications.
Key considerations include:
- Temperature control
- Protection from moisture
- Protection from unnecessary light exposure
- Appropriate vial sealing
- Minimizing repeated temperature fluctuations
- Proper documentation
- Maintaining cold-chain conditions where required
Lyophilized peptide products are generally more stable than reconstituted solutions, but stability is not unlimited.
Once a peptide is reconstituted, the storage conditions and stability considerations change substantially.
Researchers should always follow the product-specific documentation and validated stability information rather than relying on generic peptide-storage advice.
Why Peptide Purity Matters in Retatrutide vs Tirzepatide Research
This is an area where more than two decades of research-peptide experience has taught us an important lesson:
A vial can look perfect and still be analytically unsuitable for research.
NovaSyn Labs has been serving research-peptide customers for more than 20 years, with experience working with thousands of research customers, particularly across Europe and the United States.
For complex synthetic peptides such as retatrutide and tirzepatide, analytical verification is particularly important.
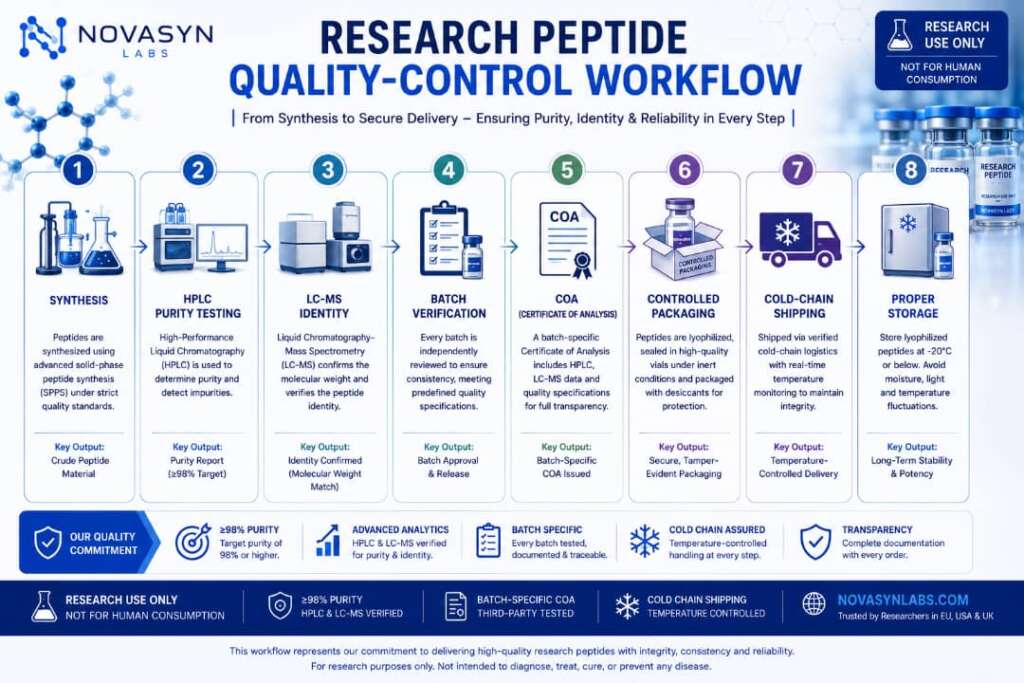
HPLC: Measuring Purity
High-performance liquid chromatography separates the target compound from related substances and synthesis impurities.
A high-purity specification—such as ≥98%—provides an important benchmark for research applications.
However, a stated purity percentage alone is not enough.
Researchers should ask:
- Was the batch actually tested?
- Is the CoA batch-specific?
- Is the chromatogram available?
- Was identity confirmed independently?
- Does the reported analytical data correspond to the exact lot supplied?
LC-MS: Confirming Identity
Mass spectrometry provides molecular-weight information that helps verify that the material corresponds to the expected peptide.
For reference, the approximate theoretical molecular weights are:
- Tirzepatide: ~4,813.5 Da
- Retatrutide: ~4,731.4 Da
HPLC and LC-MS therefore answer different questions.
HPLC: How pure is the sample?
LC-MS: Is the material consistent with the expected molecular identity?
Using both techniques creates a much stronger analytical picture.
Case Study: Tirzepatide Quality-Control Failure
A university pharmacology laboratory investigating GIP/GLP-1 receptor agonism initially purchased a bulk tirzepatide batch from a low-cost chemical broker.
The research team selected tirzepatide because it provided a useful model for studying dual GIP/GLP-1 receptor activity in rodent adipocyte cultures.
During initial experiments, however, the cells demonstrated an unexpected inflammatory response.
The supplier provided a generic in-house CoA, but the laboratory could not independently verify the analytical data.
The researchers subsequently submitted the material for independent HPLC and mass-spectrometry analysis.
The reported purity was approximately 84%, substantially below the laboratory’s target specification.
The researchers also identified unwanted contaminants that raised concerns about the suitability of the material for cellular assays.
The shipping conditions created an additional concern. The lyophilized material had been transported in basic packaging without adequate moisture protection, and the researchers suspected that environmental exposure may have contributed to degradation.
The laboratory discarded the material and sourced a replacement batch from an established supplier with independently verifiable analytical documentation.
The subsequent research was completed successfully and produced interpretable results regarding lipid accumulation and signaling pathways in the adipocyte model.
Lesson from the case
The cheapest peptide is not necessarily the lowest-cost research option.
An inadequately characterized batch can result in:
Failed experiment → wasted cells → lost laboratory time → repeat testing → replacement material → increased project cost.
Case Study: Retatrutide and Receptor-Affinity Research
A biotechnology research group investigating triple-receptor agonism was evaluating retatrutide in competitive binding assays.
The objective was to investigate receptor-affinity behavior involving:
- GLP-1 receptors
- GIP receptors
- Glucagon receptors
The team initially experienced significant supply-chain delays with an overseas vendor.
When the material eventually arrived, baseline analytical testing identified structural variation associated with incomplete sequence coupling during peptide synthesis.
Although the expected molecular mass was present, the researchers were concerned that peptide variants could affect receptor-binding measurements.
The problem became particularly important because even relatively small differences in peptide composition can introduce variability into highly sensitive binding assays.
The material had also experienced prolonged exposure to elevated temperatures during transportation after the original cold packs were depleted.
The research group subsequently changed to a specialized synthesis laboratory with stricter analytical controls and controlled cold-chain transportation.
The replacement material met the research team’s high-purity requirements and allowed the researchers to continue their receptor-affinity work.
Lesson from the case
For complex investigational peptides, identity, purity, structural consistency and transportation conditions all matter.
A peptide can pass a basic visual inspection and still fail a sophisticated research application.
How to Evaluate a Retatrutide or Tirzepatide Research Supplier
Whether you are purchasing retatrutide or tirzepatide for legitimate laboratory research, consider the supplier’s analytical documentation before considering price.
1. Batch-specific CoA
Avoid relying solely on a generic certificate.
A useful CoA should identify the actual batch or lot.
2. HPLC data
Look for an actual chromatogram rather than simply a printed purity percentage.
3. LC-MS data
Identity confirmation is particularly important for complex synthetic peptides.
4. Manufacturing information
Ask what quality systems and manufacturing controls are used.
5. Storage information
The supplier should provide appropriate storage and handling requirements.
6. Shipping protection
For temperature-sensitive research materials, packaging and transportation can be as important as the original synthesis.
7. Traceability
A reputable research supplier should be able to connect:
Product → Batch → Testing → CoA → Shipment
This creates an analytical chain of custody that researchers can document.
Research Peptide Quality-Control Checklist
| Quality factor | What researchers should look for |
| Purity | Clearly stated batch-specific result |
| HPLC | Actual chromatogram |
| LC-MS | Identity/mass confirmation |
| COA | Batch/lot-specific documentation |
| Testing | Independent verification where applicable |
| Packaging | Appropriate moisture and temperature protection |
| Storage | Clear product-specific conditions |
| Traceability | Lot-to-documentation consistency |
| Manufacturing | Documented quality framework |
| Customer support | Technical documentation available |
Retatrutide vs Tirzepatide: Cost Considerations
Cost is another major factor in research planning.
However, comparing only the price per vial can be misleading.
Consider the total cost of a successful experiment.
A low-cost peptide that contains significant impurities may lead to:
- Failed assays
- Repeat experiments
- Additional analytical testing
- Lost laboratory time
- Wasted cell cultures
- Delayed research milestones
A higher-quality material may therefore have a higher purchase price but lower overall experimental risk.
For laboratories operating under tight research budgets, cost per successful experiment may be a more useful metric than cost per vial.
Retatrutide vs Tirzepatide: Which Is Better?
There is no single answer.
If your priority is maximum demonstrated weight-loss potential:
Retatrutide is highly promising.
Its triple GIP/GLP-1/glucagon mechanism and early clinical results make it one of the most important investigational compounds in metabolic research.
If your priority is established clinical evidence:
Tirzepatide has the advantage.
It has been studied extensively across large clinical programs and has established regulatory approvals for specific indications.
If your priority is mechanism:
Retatrutide is more complex.
Three receptor targets create a broader pharmacological profile than tirzepatide’s two-target mechanism.
If your priority is long-term evidence:
Tirzepatide currently has the advantage.
Retatrutide’s long-term clinical evidence is still developing.
If your priority is research interest:
Both are exceptionally important.
Tirzepatide provides an established dual-agonist model, while retatrutide represents the next generation of multi-receptor metabolic research.
Retatrutide vs Tirzepatide: The Verdict
The most accurate conclusion is not that one compound has completely replaced the other.
Instead, think of them as two stages in the evolution of metabolic pharmacology.
Tirzepatide is the more established compound.
Its dual GIP/GLP-1 mechanism has generated extensive clinical evidence, and its regulatory status gives it a major practical advantage.
Retatrutide is the more experimental and potentially more ambitious compound.
By combining GIP, GLP-1 and glucagon receptor activity, retatrutide is designed to influence a wider range of metabolic pathways. Its early clinical results have generated considerable interest because of the magnitude of weight loss observed in clinical research.
But promising does not mean proven.
Retatrutide remains investigational, and ongoing phase 3 research will be important in determining whether its early results translate into a durable, clinically meaningful and acceptable benefit-risk profile.
Therefore, the most balanced summary of Retatrutide vs Tirzepatide is:
Retatrutide may represent the greater future weight-loss opportunity, while tirzepatide currently represents the more established clinical option.
For researchers, the comparison is equally fascinating.
Tirzepatide provides a well-characterized dual GIP/GLP-1 model, while retatrutide allows scientists to investigate what happens when glucagon receptor activity is added to the same metabolic framework.
Retatrutide vs Tirzepatide: Frequently Asked Questions
Is retatrutide stronger than tirzepatide?
Retatrutide has demonstrated very substantial weight-loss effects in clinical research, including results that appear greater than those observed with tirzepatide in some separate trials. However, there is no basis for treating these cross-trial differences as a definitive head-to-head comparison.
Is retatrutide approved for weight loss?
Retatrutide remains an investigational compound and should not be treated as an approved weight-loss medicine. Its regulatory status may change as clinical trials progress, so readers should consult current information from the relevant regulatory authority.
What is the main difference between retatrutide and tirzepatide?
Tirzepatide activates GIP and GLP-1 receptors. Retatrutide activates GIP, GLP-1 and glucagon receptors, making retatrutide a triple agonist.
Which has more clinical evidence?
Tirzepatide has substantially more established clinical evidence because it has completed a much larger development program and has received regulatory approvals for specific indications.
Does retatrutide cause gastrointestinal side effects?
Gastrointestinal adverse effects have been reported in retatrutide clinical studies. These include symptoms such as nausea, diarrhea and vomiting. The frequency can vary according to dose and study population.
How should retatrutide research material be stored?
Researchers should follow the specific manufacturer’s validated storage instructions. Temperature control, moisture protection and minimizing unnecessary temperature fluctuations are important considerations for peptide integrity.
Why are HPLC and LC-MS important?
HPLC helps characterize purity and related impurities, while LC-MS provides information supporting molecular identity. Together, they provide substantially more useful quality information than a simple purity claim.
Can retatrutide and tirzepatide be compared directly?
They can be compared mechanistically and through their respective clinical evidence, but separate clinical trials should not be treated as equivalent to a randomized head-to-head study.
Which is better for research: retatrutide or tirzepatide?
The appropriate choice depends on the research question. Tirzepatide is useful for studying dual GIP/GLP-1 activity, while retatrutide is particularly relevant to research involving combined GIP, GLP-1 and glucagon receptor activity.
Is NovaSyn Labs’ peptide material intended for human use?
No. Research peptide products discussed by NovaSyn Labs are positioned for Research Use Only (RUO) and legitimate laboratory research. They should not be represented as approved medicines or as products intended for human consumption or self-administration.
Final Thoughts
The Retatrutide vs Tirzepatide debate reflects a much larger development in metabolic science.
Tirzepatide demonstrated what could be achieved by combining GIP and GLP-1 receptor activity.
Retatrutide takes the concept further by adding glucagon receptor activity.
The result is an investigational compound that has generated exceptional interest because of its early weight-loss results.
But research should always move beyond hype.
For scientists, laboratories and research organizations, the quality of the compound matters just as much as the biological hypothesis.
A properly characterized peptide with appropriate purity, verified identity, batch-specific documentation and suitable storage conditions can make the difference between a reproducible experiment and an unexplained result.
At NovaSyn Labs, our experience spans more than 20 years of serving the research-peptide community and thousands of research customers, with extensive experience supporting researchers in Europe and the United States.
Our approach is centered on the principle that research materials should be evaluated not simply by price, but by identity, purity, documentation, handling and traceability.
As retatrutide progresses through clinical development, researchers will learn much more about whether its triple-agonist architecture can deliver the long-term advantages suggested by early studies.
For now, the evidence supports a nuanced conclusion:
Tirzepatide is more established. Retatrutide is more experimental and potentially more powerful.
And the next generation of clinical research will determine just how significant that difference ultimately becomes.
Continue Your Reading
- 5 Critical Peptide Reconstitution Mistakes That Can Ruin Your Dosage
- Why Are Peptides Lyophilized?
- Peptides Vs Steroids
External References

