







No products in the cart.

The 24-Week Retatrutide Transformation: Expectations vs. Reality

Table of Contents
Introduction: What Does a 24-Week Retatrutide Transformation Really Look Like?
Retatrutide has rapidly become one of the most closely watched compounds in obesity and metabolic research.
Sometimes described as a next-generation triple agonist, retatrutide simultaneously targets the GLP-1, GIP, and glucagon receptors. That combination has generated considerable interest because clinical research has demonstrated substantial reductions in body weight in people with obesity.
But there is a major difference between understanding a clinical-trial headline and understanding what a 24-week retatrutide transformation actually represents.
Searches for terms such as retatrutide results, retatrutide weight loss results, and retatrutide before and after can make the process appear remarkably straightforward: start treatment, lose weight every week, and reach an enormous percentage reduction by month six.
The research tells a more nuanced story.
Published clinical data demonstrate that retatrutide can produce substantial average weight reduction, particularly at higher studied doses. However, the trajectory is not perfectly linear, individual responses vary, and the dramatic results frequently discussed online need to be placed in their correct time frame.
For example, in the phase 2 obesity trial published in the New England Journal of Medicine, the highest studied groups had approximately 17.5% mean weight reduction at 24 weeks, while the 12-mg group reached approximately 24.2% at 48 weeks.
That distinction is critical.
The approximately 24% figure is a 48-week result—not a typical 24-week result.
This article examines the 24-week retatrutide transformation from three perspectives:
Published trial data → Real-world variability → Practical research interpretation
The objective is not to portray retatrutide as a miracle compound. Instead, it is to explain what the current evidence can—and cannot—tell us about retatrutide results over six months.
«Research disclaimer: Retatrutide remains an investigational compound and is not approved as a treatment for obesity or other medical conditions. This article discusses research findings and should not be interpreted as medical advice, treatment guidance, or a recommendation for human use.»
Retatrutide in Brief: Why Is It Different?
Retatrutide is being investigated as a GLP-1/GIP/glucagon receptor triple agonist.
This differentiates it mechanistically from currently established incretin therapies that primarily involve GLP-1 activity, or combinations involving GLP-1 and GIP.
The three pathways
| Receptor | General research interest |
| GLP-1 | Appetite regulation, glucose regulation and gastrointestinal effects |
| GIP | Metabolic signaling and potential complementary effects with GLP-1 |
| Glucagon | Energy metabolism and potential effects on energy expenditure |
| Triple agonism | Attempts to combine complementary metabolic mechanisms in one molecule |
The scientific interest therefore extends beyond simply suppressing appetite.
The glucagon component is particularly interesting because researchers are investigating whether it can contribute to increased energy expenditure and altered substrate metabolism while GLP-1 and GIP signaling contributes to appetite and metabolic regulation.
This is one reason triple agonist weight loss has become such an important area of research.
However, mechanism does not automatically translate into identical outcomes for every research participant.
The actual retatrutide results observed in a study depend on factors including baseline characteristics, dose, study design, adherence, duration, metabolic status and individual biological response.
What Did the 24-Week Retatrutide Clinical Trial Actually Show?
One of the most important sources for understanding retatrutide clinical trial 24-week results is the phase 2 study published in the New England Journal of Medicine.
The trial investigated adults with obesity or overweight without diabetes across several retatrutide dose groups.
The results were significant because weight reduction increased with increasing dose and continued over time.
At approximately 24 weeks, the higher-dose groups demonstrated substantial average reductions in body weight. The maximum mean reduction reported at that point was approximately 17.5%.
At 48 weeks, the 12-mg group reached approximately 24.2% mean weight reduction.
The critical distinction
| Time point | Important research finding |
| Early weeks | Weight begins changing, with considerable individual variation |
| 12 weeks | Meaningful average weight reduction becomes evident |
| 24 weeks | Highest studied groups reached approximately 17.5% mean reduction |
| 48 weeks | 12-mg group reached approximately 24.2% mean reduction |
This is why headlines can be misleading.
Someone searching for “24-week retatrutide transformation” may encounter a 24% figure and assume it represents the six-month result.
It does not.
The approximately 24% result came from the longer 48-week observation period.
Why the timeline matters
Suppose a hypothetical research participant begins at 100 kg.
A 17.5% reduction corresponds to approximately 17.5 kg, leaving a body weight of approximately 82.5 kg.
A 24.2% reduction corresponds to approximately 24.2 kg, leaving approximately 75.8 kg.
Those are dramatically different outcomes—but they occur at different study time points.
This simple comparison demonstrates why retatrutide results must always be interpreted alongside the duration of the study.
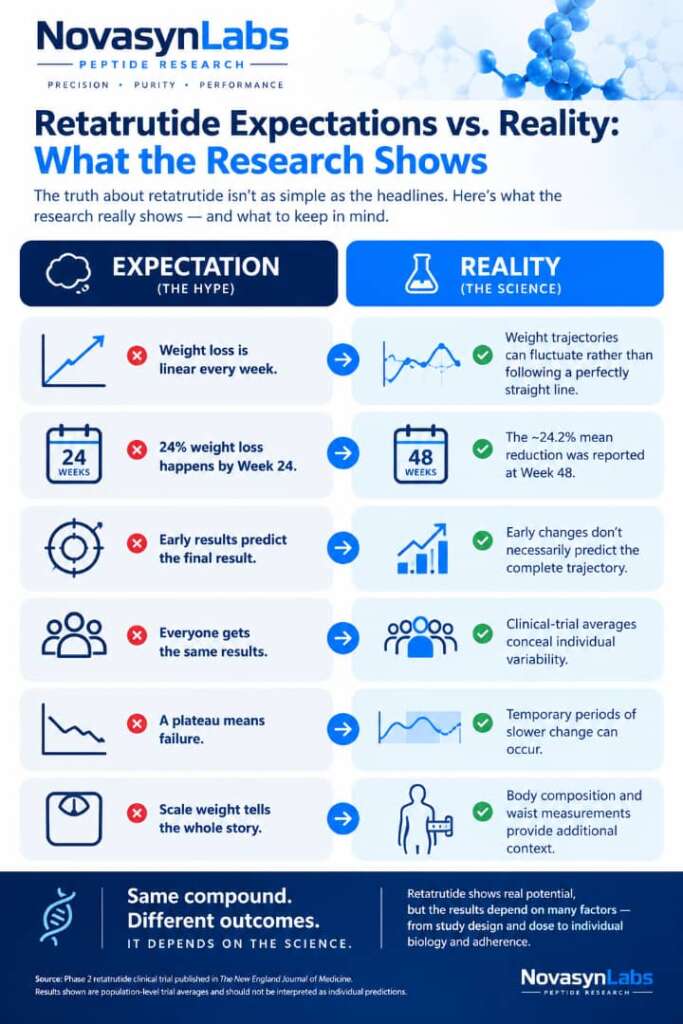
The 24-Week Retatrutide Transformation: Expectations vs. Reality
The internet tends to compress complex clinical research into simple before-and-after narratives.
The actual picture is more complicated.
Expectation #1: Weight loss should be linear every week
Reality: Weight change is rarely perfectly linear
A graph showing a smooth downward line looks convincing, but human physiology rarely behaves that neatly.
Body weight can fluctuate because of:
- Hydration
- Glycogen storage
- Gastrointestinal contents
- Sodium intake
- Dietary changes
- Physical activity
- Hormonal and metabolic adaptations
- Measurement timing
Consequently, a participant can experience several weeks of relatively little scale movement followed by a larger change.
This does not necessarily mean that the underlying biological process has completely stopped.
For research interpretation, it is generally more useful to examine multi-week trends than individual measurements.
Expectation #2: The famous 24% result happens by Week 24
Reality: The approximately 24% result was observed at Week 48
This is arguably the biggest misconception surrounding the 24-week retatrutide transformation.
The phase 2 data demonstrated approximately 17.5% mean weight reduction at 24 weeks in the highest studied groups.
The approximately 24.2% result was reported at 48 weeks in the 12-mg group.
Therefore:
24 weeks ≠ 24% weight loss.
This distinction should remain central whenever retatrutide results are discussed.
It also illustrates why comparing retatrutide with another compound requires matching:
- Study duration
- Population
- Dose
- Trial design
- Baseline characteristics
- Endpoint definitions
Otherwise, apparently comparable percentages may not actually be comparable.
Expectation #3: The first few weeks tell you exactly what the final result will be
Reality: Early changes do not necessarily predict the complete trajectory
The first several weeks of a weight-loss intervention can contain multiple components.
Changes in food intake can alter glycogen and associated water stores, while changes in gastrointestinal contents can influence scale weight.
These effects can occur alongside actual changes in fat mass.
This is why early scale changes should not automatically be interpreted as equivalent to fat loss.
In our research observations, the early phase can appear particularly dynamic, followed by a period where changes become less dramatic.
That makes the 12-to-24-week window especially important for evaluating the overall trajectory rather than focusing on isolated weekly measurements.
Expectation #4: Everyone should achieve the same retatrutide results
Reality: Biological response varies considerably
Clinical-trial averages describe populations—not individual guarantees.
Two research participants can receive the same intervention while showing different trajectories.
Potential sources of variability include:
- Baseline body composition
- Metabolic health
- Insulin sensitivity
- Dietary intake
- Physical activity
- Adherence
- Individual receptor biology
- Gastrointestinal tolerability
- Study protocol
- Duration of exposure
Consequently, an average result should never be interpreted as a promised outcome for an individual.
This principle is particularly important when evaluating online retatrutide before-and-after claims.
One dramatic example does not establish what every participant should expect.
Expectation #5: A plateau means the compound has stopped working
Reality: Short-term plateaus can occur during longer weight-loss trajectories
Weight reduction does not necessarily proceed at the same velocity throughout a study.
In observational research settings, temporary periods of slower scale change can occur around the middle of a study period.
One possible explanation is the body’s complex response to declining energy intake and body mass.
As body weight decreases, energy requirements can change. Appetite-regulatory systems and energy expenditure can also adapt.
This is commonly described as metabolic adaptation or physiological compensation.
Importantly, a short plateau should not automatically be interpreted as treatment failure.
It is more scientifically appropriate to examine the broader trajectory.
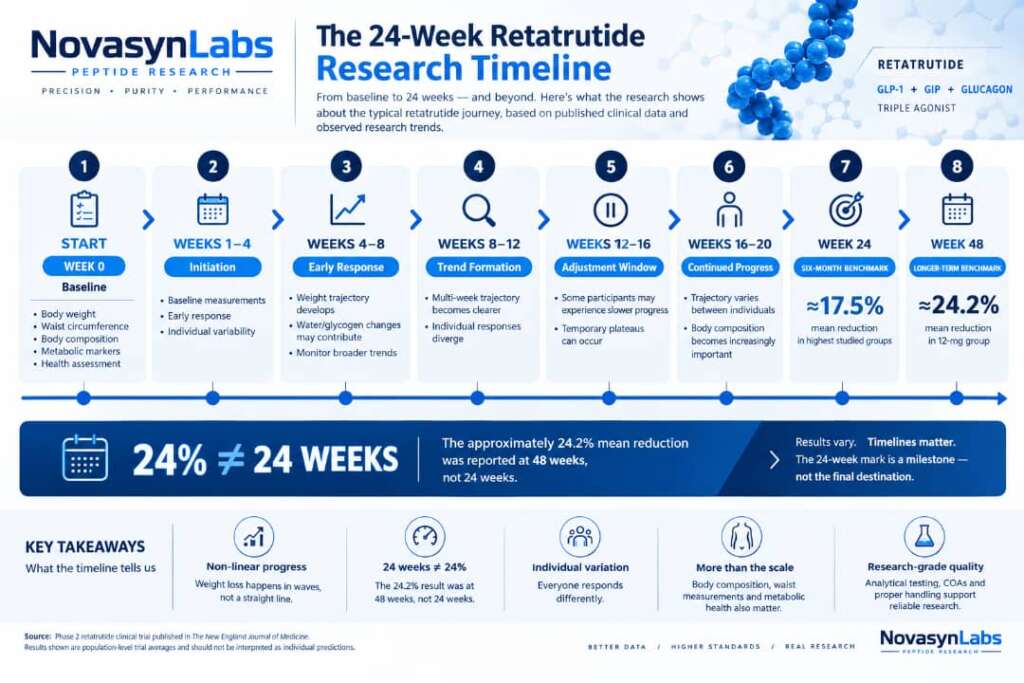
A 24-Week Retatrutide Timeline
A useful way to understand the research journey is to divide the six-month period into broad phases.
Weeks 0–4: Initiation
This is the period when researchers establish baseline measurements and begin observing the early response.
Important measurements can include:
- Body weight
- Waist circumference
- Body composition
- Food intake
- Physical activity
- Tolerability
- Metabolic markers
The key mistake is treating early scale movement as the final trajectory.
Weeks 4–8: Early Response
This phase may demonstrate more visible changes in body weight.
However, early weight changes can contain several components.
Researchers should therefore distinguish scale weight from changes in fat mass and lean mass wherever appropriate measurements are available.
Weeks 8–12: Establishing the Trend
By this point, the overall trajectory becomes more informative.
Rather than asking:
«“How much weight was lost this week?”»
researchers can ask:
«“What is the average trend over several weeks?”»
That distinction reduces the impact of normal short-term fluctuations.
Weeks 12–16: The Adjustment Window
This period can be particularly interesting.
Some research observations show temporary slowing or plateauing of weight reduction during the middle portion of a longer study.
However, this should not be treated as a universal retatrutide rule.
Individual responses vary.
Weeks 16–20: Continuing the Trajectory
Participants who continue progressing may see additional reductions in body weight.
The pace can differ substantially from the first several weeks.
This is why comparing percentage change at one isolated time point can be misleading.
Weeks 20–24: The Six-Month Benchmark
At 24 weeks, researchers have a meaningful intermediate-term data point.
The phase 2 evidence provides an important benchmark: approximately 17.5% mean weight reduction at the highest studied dose groups.
But even this number represents a population average.
It does not mean every participant reaches 17.5%.
Three Anonymized Research Profiles
Real-world observations become more useful when they demonstrate variability rather than promising a single outcome.
Profile A: The Clinical Ideal
This profile represents a relatively smooth trajectory.
The participant experiences modest early changes, followed by progressively larger reductions as the study progresses.
Around the midpoint, the trajectory accelerates following the study protocol.
By Week 24, the participant reaches approximately 18% body-weight reduction.
Research lesson
This profile resembles the upper end of the clinical-trial benchmark and demonstrates what a strong response can look like.
It should not, however, be presented as the expected result for every participant.
Profile B: Early Plateau and Adjustment
This participant experiences relatively rapid changes during Weeks 1–6.
The scale then stabilizes for approximately four weeks around the Week 12 period.
Rather than assuming failure, researchers continue monitoring the broader study trajectory.
Following the protocol’s subsequent adjustment, weight reduction resumes.
Research lesson
A temporary plateau does not necessarily mean that the overall trajectory has ended.
It demonstrates why researchers should analyze trends over time rather than reacting to individual measurements.
Profile C: High Non-Fat Mass Retention
This profile produces approximately 12% scale-weight reduction.
At first glance, this appears less dramatic than an 18% reduction.
However, body-composition analysis tells a more interesting story.
The participant combines the research intervention with resistance training and maintains a relatively favorable lean-mass profile while waist and body measurements improve.
Research lesson
Scale weight is only one metric.
For body-composition research, investigators may also want to examine:
- Lean mass
- Fat mass
- Waist circumference
- Hip circumference
- Waist-to-hip ratio
- Strength or performance measures
A smaller change on the scale does not necessarily mean a less meaningful change in body composition.
Why Body Composition Matters in a 24-Week Retatrutide Transformation
A major limitation of focusing exclusively on weight is that body weight is not a single tissue.
It includes:
- Fat mass
- Lean tissue
- Water
- Glycogen
- Bone
- Gastrointestinal contents
Therefore, two people could lose the same number of kilograms while experiencing very different body-composition changes.
This is especially relevant to researchers interested in fitness and metabolic health.
Adequate protein intake and resistance exercise are commonly investigated strategies for supporting lean-mass retention during weight loss, but their effects should not be automatically attributed to retatrutide itself.
For a scientifically rigorous 24-week analysis, the question should therefore become:
«“What changed?”»
rather than simply:
«“How much did the scale change?”»
Retatrutide vs. Tirzepatide: Why Direct Comparisons Can Be Difficult
Another high-interest search topic is retatrutide vs tirzepatide.
The comparison is understandable because both compounds involve incretin-related signaling and have generated substantial interest in obesity research.
However, indirect comparisons can easily become misleading.
To properly compare retatrutide results with tirzepatide results, researchers should consider:
| Variable | Why it matters |
| Study population | Different populations can produce different average outcomes |
| Treatment duration | 24-week and 72-week results cannot be treated as equivalent |
| Dose | Dose affects observed efficacy and tolerability |
| Trial design | Protocol differences influence outcomes |
| Baseline weight | Percentage change may interact with baseline characteristics |
| Diabetes status | Metabolic status can influence weight trajectories |
| Endpoint | Mean change is different from responder rates |
| Adherence | Actual exposure can affect observed outcomes |
Retatrutide’s triple-agonist mechanism makes it scientifically interesting, but mechanism alone does not establish superiority over another compound.
Head-to-head clinical evidence is the strongest basis for such comparisons.
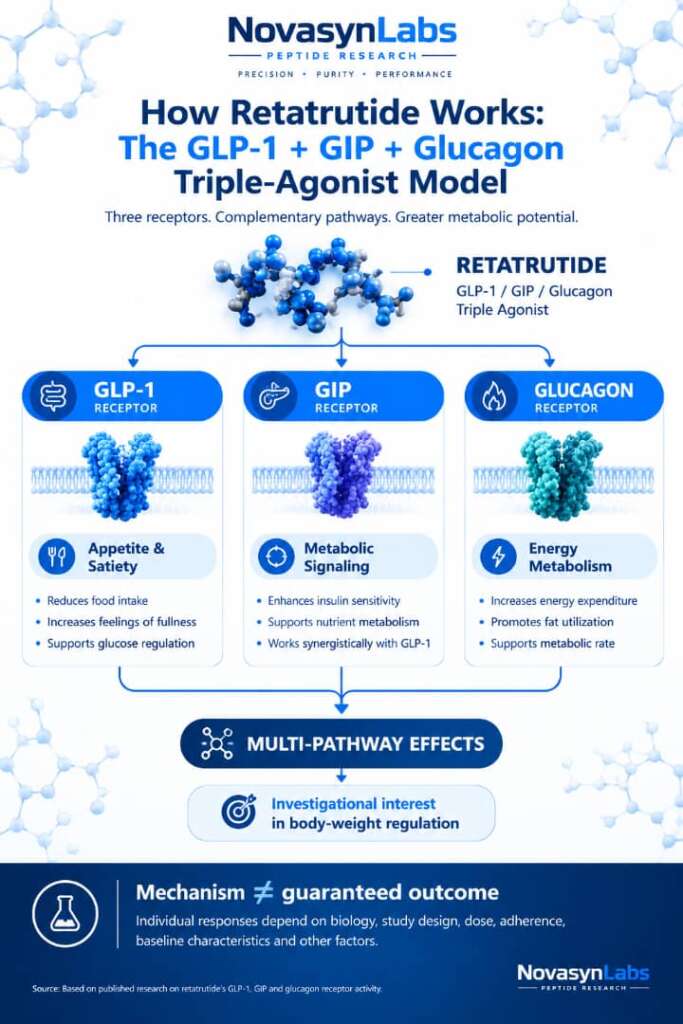
The Science Behind the Retatrutide Results
Why might triple agonism produce substantial weight reduction?
One hypothesis is that combining GLP-1, GIP and glucagon receptor activity produces complementary metabolic effects.
GLP-1 signaling
GLP-1 activity is associated with appetite regulation, satiety and glucose metabolism.
GIP signaling
GIP is being investigated for its complementary metabolic effects when combined with GLP-1 signaling.
Glucagon signaling
Glucagon has important effects on energy metabolism, and researchers are particularly interested in whether its inclusion can increase energy expenditure and influence substrate utilization.
The combined model
The scientific concept can be visualized as:
GLP-1 + GIP + Glucagon
↓
Appetite / metabolic signaling + energy metabolism
↓
Potentially greater weight reduction
But this should not be simplified into:
Triple agonist = guaranteed dramatic weight loss
Biology is considerably more complicated.
What Can Influence Retatrutide Weight Loss Results?
The same compound can produce different outcomes under different research conditions.
Several factors deserve attention.
1. Baseline characteristics
Starting weight, metabolic health, age and other characteristics can influence observed outcomes.
2. Study protocol
Dose escalation and maintenance schedules are part of the clinical-study design.
They should not be converted into generalized self-administration instructions.
3. Dietary intake
Energy intake naturally influences changes in body weight.
Reduced appetite can indirectly affect calorie consumption, but dietary composition also matters for body composition.
4. Physical activity
Activity levels can influence energy expenditure and preservation of lean tissue.
5. Adherence
Missing interventions or deviating from a research protocol can affect results.
6. Measurement methodology
A scale provides one measurement.
DEXA, bioimpedance, waist circumference and other methods provide different types of information and have their own limitations.
How NovaSynLabs Approaches Research-Grade Peptide Quality
The biological question is only one part of peptide research.
Material quality matters too.
At NovaSynLabs, the emphasis is on analytical verification and controlled handling rather than marketplace hype.
Our research-grade quality framework includes:
HPLC verification
High-Performance Liquid Chromatography is used as an analytical method for assessing peptide purity.
NovaSynLabs research materials are specified at ≥98% purity, with analytical verification supporting the stated specification.
LC-MS confirmation
Mass spectrometry provides molecular-mass information that can complement chromatographic purity analysis.
Using both approaches creates a stronger analytical framework than relying on a single marketplace claim.
Batch-specific COAs
A Certificate of Analysis provides batch-level documentation.
For researchers, batch-specific documentation is important because it connects the analytical result to the actual material being evaluated.
Lyophilized format
Lyophilization, or freeze-drying, removes water from the material under controlled conditions and can improve storage stability for many peptide materials.
Temperature-controlled handling
Research peptides can be sensitive to environmental conditions.
NovasynLabs therefore emphasizes temperature-controlled packaging and cold-chain handling during shipping.
For research storage, product-specific instructions and the relevant COA should always take precedence. General storage information commonly used for these materials includes approximately -20°C for longer-term storage and appropriate refrigerated conditions for reconstituted material where specified.
Trial Headlines vs. Research Reality
The difference between a headline and the underlying evidence can be summarized like this:
| Online expectation | Evidence-based interpretation |
| “24% weight loss in six months” | The ~24% result was reported around 48 weeks, not 24 weeks |
| “Weight drops every week” | Weight trajectories naturally fluctuate |
| “Everyone gets the same result” | Clinical averages conceal individual variability |
| “A plateau means failure” | Short-term plateaus can occur during weight-loss trajectories |
| “Scale weight tells everything” | Body composition provides additional information |
| “Triple agonist means guaranteed superiority” | Comparative conclusions require appropriate clinical evidence |
| “Early weight loss equals fat loss” | Early scale changes can include water and glycogen shifts |
| “More dramatic is always better” | Lean-mass retention and body composition also matter |
What Should Researchers Look for at Week 24?
A strong six-month research assessment should go beyond a single percentage.
Consider evaluating:
Body weight
What is the percentage and absolute change from baseline?
Body composition
How much of the change appears attributable to fat mass versus lean mass?
Waist circumference
Has central adiposity changed?
Metabolic markers
Where appropriate, what changes are observed in relevant biomarkers?
Adherence
Was the research protocol followed consistently?
Tolerability
What adverse effects or limitations affected the study?
Trajectory
Was the change consistent, fluctuating, or interrupted by a plateau?
Context
How do the results compare with the relevant clinical-trial population?
This creates a much more meaningful 24-week retatrutide transformation than a simple before-and-after photograph.
The Biggest Lesson From 24 Weeks of Retatrutide Research
Perhaps the most important lesson is that time changes the interpretation of the numbers.
A 17.5% average reduction at 24 weeks and a 24.2% average reduction at 48 weeks are not competing claims.
They represent different points along a longer research trajectory.
Likewise, a participant showing 12% weight reduction at 24 weeks should not automatically be considered a poor responder simply because another participant achieved 18%.
The research question should be:
What happened, under what conditions, over what period, and how was it measured?
That mindset is much more useful than chasing a single headline number.
24-Week Retatrutide Transformation: Expectations vs. Reality
The current evidence supports a more nuanced interpretation of retatrutide.
Expectation
Retatrutide produces an identical, perfectly linear transformation.
Reality
Weight reduction can fluctuate and individual trajectories vary.
Expectation
The approximately 24% clinical-trial figure occurs by Week 24.
Reality
The approximately 24.2% mean reduction was observed at Week 48 in the 12-mg group, while the highest studied groups reached approximately 17.5% at Week 24.
Expectation
Scale weight is the only important outcome.
Reality
Body composition, waist measurements, metabolic outcomes and lean-mass retention can provide additional information.
Expectation
Mechanism guarantees superiority.
Reality
Retatrutide’s triple-agonist mechanism is scientifically promising, but comparative claims require appropriate clinical evidence.
Final Takeaway
The 24-week retatrutide transformation is best understood as an intermediate milestone—not a finish line.
The phase 2 clinical evidence demonstrated substantial average weight reduction by Week 24, with approximately 17.5% mean reduction in the highest studied groups. The much-discussed approximately 24.2% reduction occurred at Week 48 in the 12-mg group.
That distinction matters.
The real story behind retatrutide results is not simply how much weight can disappear from the scale. It is how the trajectory develops, how individual responses differ, how body composition changes, and how those observations compare with controlled clinical research.
For researchers evaluating retatrutide, analytical rigor should extend beyond the compound itself. Material identity, purity, batch documentation, storage, handling and temperature control all contribute to a more reliable research process.
At NovaSynLabs, our focus is on those fundamentals: research-grade material standards, ≥98% purity specifications, HPLC and LC-MS analytical verification, batch-specific COAs and controlled handling practices.
Researchers interested in evaluating retatrutide should prioritize documented analytical quality rather than relying solely on marketplace claims or dramatic before-and-after narratives.
For research purposes, the best question isn’t “How dramatic will the transformation be?”
It is:
“What does the evidence show, how was the result measured, and can the research material itself be analytically verified?”
That is the difference between following a peptide headline and understanding the science behind it.
Research-use-only disclaimer: Retatrutide is an investigational compound and is not approved for human therapeutic use. The information presented here is intended for educational and research discussion only and should not be interpreted as medical advice, dosing guidance, or a recommendation for human use.
External References

