







No products in the cart.

The Truth About Semaglutide: How Much Weight Do People Actually Lose?

Table of Contents
How Much Weight Do People Actually Lose on Semaglutide?
Semaglutide has transformed the conversation around obesity and metabolic research. But one question continues to dominate online searches:
How much weight do people actually lose on Semaglutide?
The answer is more complicated than many headlines suggest.
Some people lose more than 15% or even 20% of their starting body weight. Others experience considerably less weight reduction. Some discontinue treatment before reaching the later stages of treatment. And when Semaglutide is stopped, a substantial amount of previously lost weight can return.
Clinical trials provide the clearest benchmark. In the landmark STEP 1 trial, adults with overweight or obesity who received once-weekly Semaglutide 2.4 mg alongside lifestyle intervention achieved an average weight reduction of approximately 14.9% after 68 weeks, compared with approximately 2.4% with placebo.
That does not mean every person loses 15%.
It means that the average response in a specific clinical-trial population was around that level under controlled conditions.
Real-world results can be different.
Observational studies have reported lower average weight reductions in routine practice, often reflecting differences in treatment persistence, dose escalation, access, side effects, patient characteristics, and lifestyle changes.
So what is the realistic answer?
For many people, thinking in terms of percentage of starting body weight is more useful than expecting a fixed number of pounds or kilograms.
| Starting Weight | 5% Loss | 10% Loss | 15% Loss | 20% Loss |
| 150 lb | 7.5 lb | 15 lb | 22.5 lb | 30 lb |
| 180 lb | 9 lb | 18 lb | 27 lb | 36 lb |
| 200 lb | 10 lb | 20 lb | 30 lb | 40 lb |
| 220 lb | 11 lb | 22 lb | 33 lb | 44 lb |
| 250 lb | 12.5 lb | 25 lb | 37.5 lb | 50 lb |
| 300 lb | 15 lb | 30 lb | 45 lb | 60 lb |

This is why saying “Semaglutide causes 30 pounds of weight loss” can be misleading. Thirty pounds represents a very different percentage reduction for someone starting at 150 pounds compared with someone starting at 300 pounds.
Clinical Trial Results vs Real-World Semaglutide Weight Loss
One of the biggest mistakes people make when researching Semaglutide is assuming that clinical-trial results are guaranteed individual outcomes.
They aren’t.
Clinical trials have carefully selected participants, structured follow-up, defined treatment protocols, and lifestyle interventions. Real-world populations are much more diverse.
Semaglutide: Clinical vs Real-World Results
| Measure | Clinical Trial Environment | Real-World Environment |
| Treatment adherence | Closely monitored | Highly variable |
| Dose escalation | Structured | May be slower or interrupted |
| Follow-up | Regular | Variable |
| Lifestyle support | Often structured | Variable |
| Side effects | Monitored | May lead to discontinuation |
| Average weight reduction | Around 15% in STEP 1 at 68 weeks | Often lower in observational studies |
| Individual response | Wide variation | Wide variation |
| Treatment persistence | Generally high | Can be substantially lower |
Real-world observational data can therefore show average weight loss closer to the 8–12% range at around six months in some populations, although results vary considerably between studies.
This distinction matters.
Someone searching “Semaglutide average weight loss percentage” should understand that there is no single percentage applicable to everyone.

How Fast Do You Lose Weight on Semaglutide?
Another common misconception is that Semaglutide produces dramatic weight loss immediately.
It generally doesn’t.
Early treatment is typically a period of adjustment. Clinical regimens use gradual escalation to improve tolerability, particularly gastrointestinal tolerability.
Consequently, the first several weeks should not necessarily be compared with the eventual results observed after many months.
A Simplified Semaglutide Weight-Loss Timeline
| Period | What May Happen |
| First several weeks | Appetite changes may begin; weight response varies |
| Early treatment | Gradual adjustment and dose escalation |
| Several months | More noticeable cumulative weight reduction may occur |
| 6 months | Real-world results can vary substantially |
| 12+ months | Greater cumulative weight reduction may be observed in persistent responders |
| Around 68 weeks | STEP 1 provides an important clinical-trial benchmark |
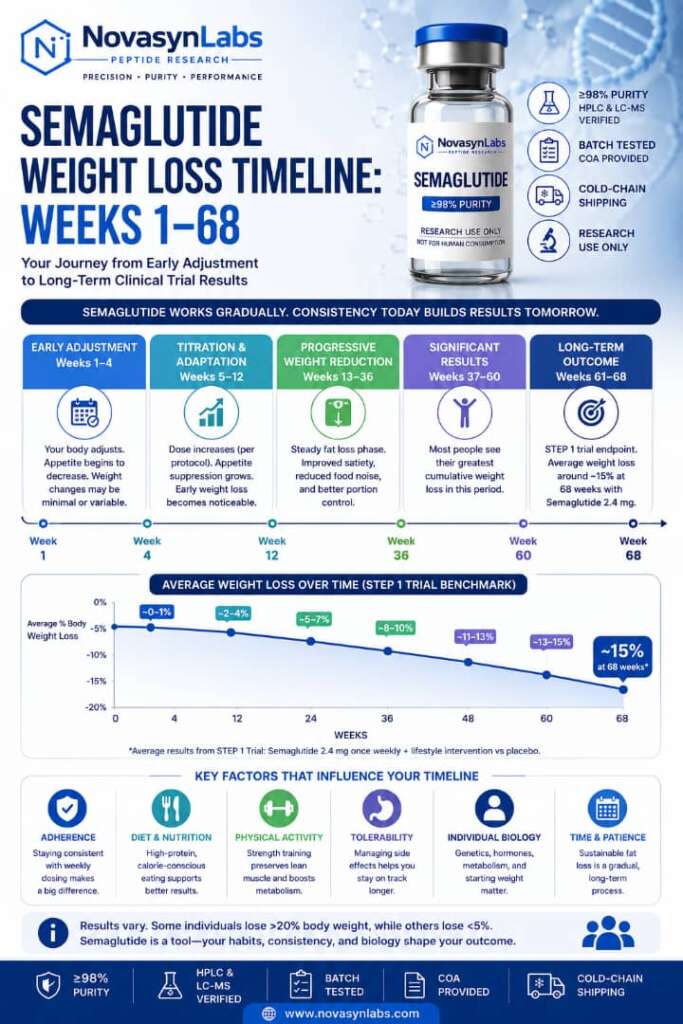
The most important point is that Semaglutide weight loss is a long-term process rather than a one-week transformation.
People who expect to lose 5–10 pounds every week are setting themselves up for unrealistic expectations.
Why Does Semaglutide Cause Weight Loss?
Semaglutide is a GLP-1 receptor agonist.
GLP-1, or glucagon-like peptide-1, is a naturally occurring hormone involved in appetite regulation, glucose metabolism, and gastrointestinal function.
Semaglutide activates GLP-1 receptors and can influence several physiological processes relevant to body weight.
These include:
- Increased feelings of fullness
- Reduced appetite
- Reduced food intake
- Slower gastric emptying, particularly earlier in treatment
- Effects on central appetite-regulation pathways
- Improved glucose regulation in appropriate clinical populations
The result is not simply that Semaglutide “melts fat.”
Instead, changes in appetite, satiety, food intake, and metabolic regulation can make it easier for some people to sustain a calorie deficit.
That distinction is important.
Semaglutide does not make the laws of energy balance disappear.
If energy intake consistently exceeds energy expenditure, meaningful fat loss is unlikely to continue indefinitely.
Does Everyone Lose 15–20% of Their Weight?
No.
This is one of the most important truths about Semaglutide.
Clinical averages hide substantial individual variation.
A person may experience a very large response, a moderate response, a small response, or discontinue treatment before reaching the point where maximum weight reduction would have occurred.
Three Anonymized Real-World Examples
The following examples are anonymized reports provided for educational illustration. They should not be interpreted as clinical trials conducted by NovaSyn Labs or as evidence that these outcomes are typical.
Case Study 1: A High Responder
Starting weight: 235 lb
Reported BMI: 36.8
Duration: Approximately 14 months
Reported weight loss: 49 lb
Percentage reduction: Approximately 20.8%
This individual reported reaching the maximum target dose used in their treatment plan and maintained high adherence.
They also reported substantial appetite suppression and a major reduction in what they described as persistent “food noise.”
Importantly, Semaglutide was not the only factor involved.
The individual combined treatment with:
- A structured high-protein eating pattern
- Resistance training
- Consistent adherence
- Long-term lifestyle changes
The result was approximately 49 pounds of reported weight reduction.
This illustrates what is possible for a strong responder, but it should not be interpreted as a promise that someone else will lose 20% of their starting weight.
Case Study 2: A Moderate Real-World Responder
Starting weight: 198 lb
Reported BMI: 32.0
Duration: Approximately 6 months
Reported weight loss: 18 lb
Percentage reduction: Approximately 9.1%
This example looks quite different.
The individual remained at a lower treatment level because of gastrointestinal sensitivity and did not progress to the highest target dose.
Nevertheless, they reported approximately 18 pounds of weight reduction over six months.
That represents roughly 9.1% of their starting body weight.
This case is useful because it demonstrates why clinical-trial averages should not be interpreted as individual targets.
A person does not necessarily need to achieve the maximum possible treatment exposure to experience meaningful changes, and tolerability can influence how treatment progresses in real-world settings.
Case Study 3: A Low Responder
Starting weight: 215 lb
Reported BMI: 34.7
Duration: Approximately 6 months
Reported weight loss: 5 lb
Percentage reduction: Approximately 2.3%
This individual reported relatively little appetite reduction.
Persistent nausea also contributed to early discontinuation before completing the planned escalation process.
The resulting weight reduction was approximately 5 pounds, or 2.3% of starting weight.
This is perhaps the most important case of the three.
Not everybody responds dramatically.
Including low-response examples makes the discussion of Semaglutide more realistic and prevents readers from assuming that every person will reproduce the best results seen in clinical trials.
What Percentage of Semaglutide Users Are Non-Responders?
The term “non-responder” requires caution.
There isn’t one universally accepted definition, and the percentage depends on the population, treatment duration, endpoint, and definition being used.
Some analyses identify a relatively small proportion of participants who fail to achieve clinically meaningful weight reduction. A useful practical concept is people losing less than 5% of baseline body weight, although that should not automatically be equated with complete biological non-response.
Individual response can be affected by:
- Baseline metabolic health
- Genetic factors
- Treatment persistence
- Tolerability
- Lifestyle
- Underlying disease
- Concomitant medications
- Appetite response
- Duration of treatment
Consequently, quoting a precise “Semaglutide non-responders percentage” without defining the population can be misleading.
Why Do Some People Lose More Weight Than Others?
Semaglutide response is not determined by one variable.
1. Baseline metabolic health
People with obesity but without diabetes may experience somewhat greater average percentage weight reduction than populations with type 2 diabetes, although individual outcomes overlap substantially.
2. Treatment persistence
Someone who stops treatment early cannot be expected to have the same cumulative response as someone who remains in treatment for a longer period.
3. Tolerability
Gastrointestinal adverse effects can affect adherence and treatment continuation.
4. Lifestyle
Dietary quality, physical activity, sleep, and behavioral patterns can all influence the overall trajectory.
5. Starting weight
Percentage change and absolute pounds lost are not the same measurement.
6. Individual biology
People differ in appetite regulation, metabolic physiology, genetics, and response to medications.
This is why a single Semaglutide weight-loss number should always be treated as a population average rather than an individual guarantee.
Does a Higher Semaglutide Dose Always Mean More Weight Loss?
Not necessarily.
Clinical research demonstrates a relationship between treatment exposure and weight reduction at the population level, but that does not mean doubling exposure produces double the rate of weight loss in an individual.
More importantly, treatment escalation has to be considered alongside tolerability and clinical appropriateness.
A person who experiences significant gastrointestinal effects may have difficulty maintaining treatment.
Therefore, more is not automatically better.
This is another reason why online discussions that focus exclusively on the highest dose can give readers an unrealistic picture of how Semaglutide treatment works.
What Happens When You Stop Semaglutide?
This is arguably the most overlooked part of the Semaglutide weight-loss discussion.
Losing weight is only one part of the story.
Maintaining that weight reduction is another.
In the STEP 1 extension, participants who discontinued Semaglutide regained a substantial proportion of their previously lost weight during the following year. Approximately two-thirds of the weight they had lost was regained by the one-year follow-up.
This does not mean that every person will regain exactly two-thirds.
It demonstrates something more fundamental:
The biological drivers of appetite and body-weight regulation do not permanently disappear simply because someone has lost weight.
When Semaglutide is discontinued, its pharmacological effects gradually wear off.
Appetite may increase again.
Food intake may rise.
The physiological pressures that favor weight regain can return.
Why Does Weight Regain Happen?
Body weight is biologically regulated.
After substantial weight loss, the body can respond through mechanisms that increase hunger and reduce energy expenditure.
This is sometimes described as metabolic adaptation.
The individual may therefore face:
- Increased appetite
- Reduced satiety
- Increased food cravings
- Lower energy expenditure
- Changes in hormones involved in hunger and satiety
- Behavioral challenges associated with maintaining a lower body weight
Semaglutide can modify some of the appetite-related signals while it is active.
Once treatment is discontinued, those effects can diminish.
This is why long-term weight management cannot simply be viewed as “taking a drug until the scale reaches a target number.”
Semaglutide vs Tirzepatide: Which Produces More Weight Loss?
The rise of Tirzepatide has created another major question:
Is Semaglutide still the most effective GLP-1-based option for weight loss?
Not necessarily.
Tirzepatide acts on both the GLP-1 and GIP receptors, whereas Semaglutide primarily targets the GLP-1 receptor.
Clinical trials have generally demonstrated greater average weight reduction with Tirzepatide than Semaglutide in comparable obesity-treatment contexts.
However, cross-trial comparisons need caution because different studies can have different participants, durations, treatment protocols, and endpoints.
Semaglutide vs Other Weight-Loss Compounds
| Compound | Main Target(s) | Approximate Clinical Weight-Loss Benchmark |
| Liraglutide | GLP-1 | ~8% |
| Semaglutide | GLP-1 | ~15% |
| Tirzepatide | GLP-1 + GIP | ~20% |
| Retatrutide | GLP-1 + GIP + glucagon | Up to ~24%+ in investigational research |
| CagriSema | Amylin analogue + GLP-1 | Investigational combination |
These numbers are not head-to-head guarantees.
Retatrutide, for example, remains investigational, and results from clinical research should not be interpreted as established real-world treatment outcomes.
The broader lesson is that obesity research is moving beyond single-pathway GLP-1 agonism toward increasingly complex combinations and multi-receptor approaches.
Semaglutide Clinical Trials vs Real-World Results: Why Is There a Difference?
A clinical trial might report approximately 15% average weight loss after 68 weeks.
A real-world population might show a lower average percentage after six months.
That isn’t necessarily contradictory.
Consider what happens outside a controlled trial.
Some people:
- Miss doses
- Stop treatment early
- Never reach later treatment stages
- Experience side effects
- Have limited dietary support
- Have different metabolic conditions
- Cannot maintain treatment long term
- Receive inconsistent product quality when using unverified research materials
Clinical-trial participants generally receive substantially more structured monitoring than the average person searching online for weight-loss information.
Therefore, the phrase “Semaglutide real-world results vs clinical trials” deserves much more attention than a simple comparison of two percentages.
Why Product Quality Matters in Peptide Research
There is another issue that deserves attention, particularly from a research perspective: analytical quality.
The growing demand for GLP-1-related compounds has created an environment in which buyers can encounter poorly characterized or improperly handled materials.
Potential problems include:
- Missing Certificates of Analysis
- Incorrect labeling
- Inadequate analytical characterization
- Poor storage conditions
- Temperature excursions
- Degradation
- Batch inconsistency
- Products from suppliers without transparent quality documentation
One anonymized research-laboratory report illustrates the problem.
A laboratory reported inconsistent assay results after purchasing low-cost Semaglutide from an unverified overseas supplier. Subsequent independent LC-MS analysis reportedly indicated substantial degradation of the material.
The laboratory switched to a high-purity, COA-verified batch and subsequently reported improved analytical consistency.
The lesson is important:
When experimental results look unusual, researchers should consider material identity, purity, degradation, storage, and analytical variability rather than automatically assuming that the biological system is responsible.
For research applications, analytical documentation is therefore an important part of evaluating peptide materials.
NovaSyn Labs’ Approach to Research-Grade Semaglutide
NovaSyn Labs brings more than 20 years of experience supplying high-purity research materials and peptides to customers across Europe and the United States.
The company has served thousands of research customers and orders worldwide across academic, private, and institutional laboratory settings.
For research applications, NovaSyn Labs’ Semaglutide is supplied as a lyophilized research material with batch-specific analytical documentation.
The stated specifications include:
| Research Material Characteristic | NovaSyn Labs Specification |
| Form | Lyophilized/freeze-dried powder |
| Vial format | Sealed amber glass |
| Available quantities | 2 mg, 5 mg, 10 mg |
| Purity specification | ≥98% |
| Analytical methods | HPLC and LC-MS |
| Documentation | Batch-specific COA |
| Shipping | Insulated temperature-controlled packaging |
| Long-term storage | -20°C, protected from light |
| Intended use | Research Use Only |
NovaSyn Labs’ positioning is deliberately focused on research applications, not human consumption.
The company does not provide human dosing instructions, medical advice, or therapeutic guarantees for research materials.
That distinction matters.
A research peptide supplier should not blur the line between laboratory materials and approved medical treatment.
The Biggest Myths About Semaglutide Weight Loss
Myth 1: “Everyone loses 20%.”
Reality: Some participants achieve very large reductions, but individual responses vary considerably.
Myth 2: “You lose weight immediately.”
Reality: Early treatment can involve gradual changes, and substantial cumulative weight loss generally develops over months rather than days.
Myth 3: “Semaglutide melts fat.”
Reality: Its major weight-related effects involve appetite, satiety, food intake, and metabolic regulation.
Myth 4: “A higher dose guarantees faster results.”
Reality: Dose-response relationships exist at the population level, but individual outcomes and tolerability vary.
Myth 5: “The weight stays off automatically.”
Reality: Clinical follow-up after discontinuation demonstrates substantial weight regain in many participants.
Myth 6: “If Semaglutide doesn’t work, the product must be fake.”
Reality: Biological response varies. However, product identity, purity, degradation, storage, and analytical quality should also be considered in legitimate research settings.
So, How Much Weight Do People Actually Lose on Semaglutide?
If you want the simplest evidence-based answer, it is this:
Semaglutide can produce substantial weight loss, but there is no single amount that everyone should expect.
A major clinical-trial benchmark is approximately 15% average body-weight reduction after 68 weeks with Semaglutide 2.4 mg in the STEP 1 population.
Real-world outcomes can be lower, particularly over shorter periods, with observational data often showing approximately 8–12% reduction around six months in some populations.
Some individuals lose more than 20%.
Others lose considerably less.
And some discontinue treatment before reaching their maximum potential response.
The most useful way to think about Semaglutide is therefore not:
“How many pounds will Semaglutide make me lose?”
but:
“What percentage of starting body weight is realistic for a population like mine, over what period, and what factors determine whether that response is maintained?”
That is a much more scientifically meaningful question.
Frequently Asked Questions About Semaglutide Weight Loss
How much weight can you lose on Semaglutide?
Clinical-trial participants receiving Semaglutide 2.4 mg alongside lifestyle intervention achieved approximately 15% average weight loss after 68 weeks in STEP 1. Individual results vary considerably.
How fast do you lose weight on Semaglutide?
Weight loss generally develops progressively rather than occurring immediately. Early treatment involves adjustment and gradual escalation, while larger cumulative reductions can develop over many months.
Can you lose 20% of your body weight with Semaglutide?
Yes, some people achieve 20% or more, but this is not an outcome everyone should expect. Individual response varies.
What percentage of Semaglutide users don’t respond?
There is no single universally accepted non-responder percentage because definitions and study populations differ. Some people experience less than 5% weight reduction, while others experience much larger responses.
What happens when you stop Semaglutide?
Clinical follow-up indicates that substantial weight regain can occur after discontinuation. In the STEP 1 extension, participants regained approximately two-thirds of their prior weight loss over the following year.
Is Semaglutide better than Tirzepatide for weight loss?
Clinical trials generally show greater average weight reduction with Tirzepatide, although direct comparisons should be interpreted using appropriate head-to-head evidence rather than simply comparing separate trials.
Does Semaglutide work without diet and exercise?
Semaglutide can reduce appetite and food intake, but lifestyle factors remain important components of weight management. Clinical trials also commonly include lifestyle intervention.
Why do some people lose very little weight?
Potential factors include individual biology, treatment persistence, tolerability, underlying metabolic conditions, lifestyle factors, and insufficient treatment duration. In research settings, material identity and analytical quality should also be verified when experimental results are unexpectedly inconsistent.
Final Takeaway
The truth about Semaglutide is neither that it is a miracle drug nor that the headline numbers are meaningless.
The clinical evidence shows that Semaglutide can produce clinically significant weight reduction, with approximately 15% average weight loss demonstrated in a major 68-week clinical trial.
But averages are not guarantees.
Some people achieve 20% or more. Others experience moderate results around 8–12%. A smaller group may lose less than 5%, and some discontinue treatment because of tolerability or other factors.
Just as importantly, weight loss is not necessarily permanent after treatment stops. Long-term weight management involves biological, behavioral, and environmental factors that continue after the medication is discontinued.
For researchers, there is another lesson: the quality and stability of the material being studied matters. Proper analytical characterization, batch documentation, purity testing, storage, and handling are essential when interpreting experimental findings.
Backed by more than 20 years of experience supplying research-grade peptides and high-purity research materials to thousands of laboratories across Europe and the United States, NovaSyn Labs approaches Semaglutide from a research-quality perspective: documented analytical standards, batch consistency, and transparent research-use positioning.
Ultimately, the most accurate answer to “How much weight do people actually lose on Semaglutide?” is:
There is a wide range of outcomes, but approximately 15% average weight loss over 68 weeks is one of the strongest clinical benchmarks available—while real-world results can be lower, higher, or substantially different for individual people.
That distinction between average clinical results and individual reality is the real truth about Semaglutide weight loss.
External References

